What Tests Are Needed Before Bariatric Surgery?
Most candidates complete blood work (complete blood count, metabolic panel, glucose and HbA1c, lipid panel, thyroid function), nutritional screening (iron, ferritin, vitamin B12, folate, vitamin D, calcium), an electrocardiogram, and program-specific assessments such as upper endoscopy, sleep apnea screening, and psychological evaluation. Your surgical team adds or removes tests based on your medical history, the planned procedure, and current clinical guidelines.
Bariatric surgery changes how your body processes food, so your care team needs a complete picture of your health before the operation. A structured preoperative bariatric evaluation protects you during anesthesia, reveals conditions that need treatment first, and creates baseline measurements for lifelong follow-up care. Major clinical guidelines describe this evaluation as a mandatory step, not an optional formality (Mechanick et al. 2020). The sections below follow the actual sequence of a bariatric workup, from routine laboratory panels to specialized investigations.
Why Is Medical Testing Important Before Weight Loss Surgery?
Preoperative testing detects hidden problems that raise anesthesia and surgical risk, uncovers nutrient deficiencies that need correction, and gives your team the data to build an individualized treatment plan.
Large registries show that careful patient selection keeps serious complication rates low. The Longitudinal Assessment of Bariatric Surgery consortium reported a 30-day major complication rate of roughly 4 percent across thousands of operations, a figure that reflects disciplined preoperative screening (Flum et al. 2009). A later systematic review confirmed that risk varies strongly with patient health status, which makes individualized evaluation essential (Chang et al. 2018).
Testing serves three concrete purposes. First, it flags cardiopulmonary and metabolic conditions that demand optimization before anesthesia. Second, it reveals iron, vitamin, and protein deficiencies that would worsen after surgery if left untreated. Third, it records baseline values. After the operation, your team compares new results against these baselines to spot malnutrition early. Each purpose feeds the next, and laboratory analysis forms the foundation of the entire process.
Which Blood Tests Are Required Before Bariatric Surgery?
Nearly every program orders a complete blood count, a comprehensive metabolic panel, blood glucose with HbA1c, a lipid profile, and thyroid function tests. Coagulation studies and urinalysis are added when your history or medications call for them.
Blood work forms the core of bariatric surgery clearance because it is inexpensive, fast, and revealing. Guidelines endorse routine biochemical screening for every candidate (Mechanick et al. 2020). The table below shows what each panel measures and why it matters.
Test | What it measures | Why your team orders it |
Complete Blood Count (CBC) | Red cells, white cells, platelets | Detects anemia and infection risk |
Comprehensive Metabolic Panel (CMP) | Kidney and liver function, electrolytes, glucose, protein | Confirms organs tolerate anesthesia and surgery |
Blood Glucose and HbA1c | Current sugar and three-month average | Judges diabetes control and healing risk |
Lipid Profile | Cholesterol and triglycerides | Gauges cardiovascular and metabolic risk |
Thyroid Function Tests | TSH, with T3 or T4 when indicated | Uncovers thyroid disorders that affect weight and heart rate |
Coagulation Tests | Clotting time and factors | Guides bleeding risk when history or drugs warrant |
Urinalysis | Urine chemistry and cells | Screens for kidney issues, infection, or glucose spillage |
Abnormal values rarely cancel surgery. Instead, they trigger treatment. Uncontrolled glucose, for example, usually leads to medication adjustment and a repeat test before the team grants clearance. Because blood draws also supply the first nutritional data, the laboratory panel leads directly into micronutrient screening.
What Vitamin and Nutritional Tests Are Needed Before Surgery?
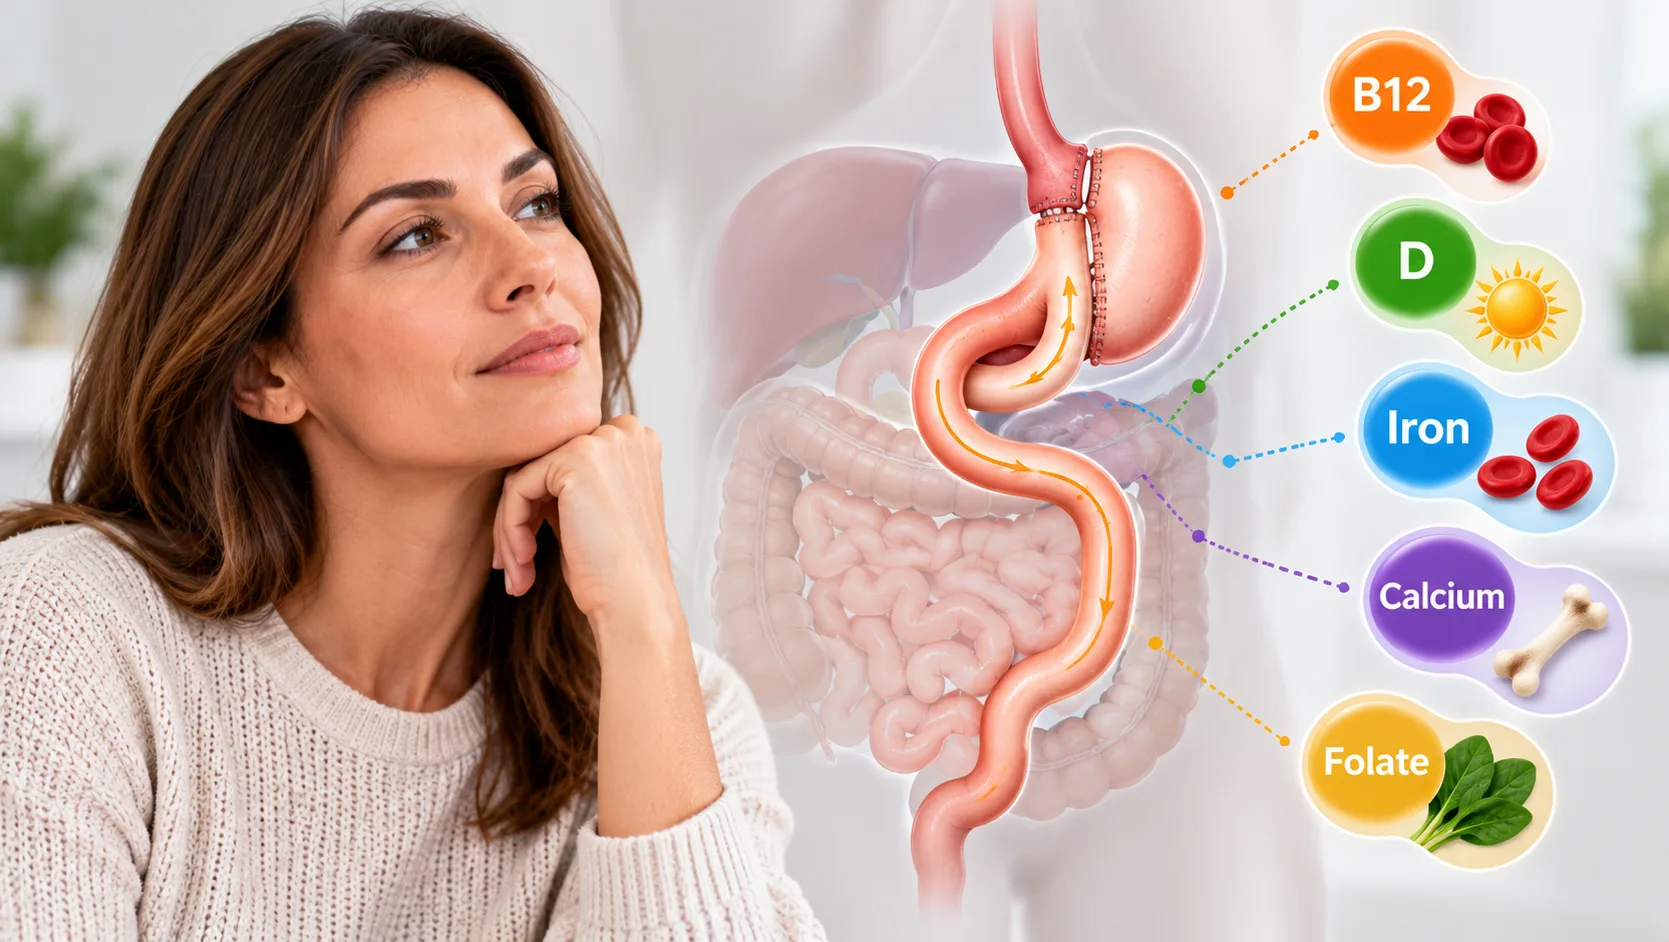
Expect testing for iron and ferritin, vitamin B12, folate, vitamin D, and calcium, often with parathyroid hormone. Some programs add thiamine, zinc, or copper based on symptoms and dietary history.
People with obesity frequently carry hidden micronutrient deficiencies before any operation. In one cohort of sleeve gastrectomy patients, nearly all participants showed low vitamin D, while iron, folate, and B12 deficits appeared in a substantial minority (Ben-Porat et al. 2015). British guidelines recommend preoperative measurement of iron, ferritin, B12, folate, calcium, and vitamin D for all candidates (O'Kane et al. 2020).
These results serve two functions. They guide correction before surgery, because healing demands adequate iron, protein, and vitamins. They also establish the reference points for postoperative monitoring, when reduced food intake and altered absorption raise deficiency risk. Correcting a low ferritin level before the operation, for instance, lowers the chance of postoperative anemia. With nutritional status secured, attention turns to the organs that must withstand anesthesia.
Which Heart and Lung Tests May Be Needed?
An electrocardiogram is routine for most candidates. Echocardiograms, stress tests, chest X-rays, and pulmonary function tests are ordered only when symptoms or risk factors justify them.
The goal is fitness for anesthesia, not a cardiac deep dive for every patient. A resting electrocardiogram records the heart's electrical rhythm and exposes arrhythmias or silent ischemia. When risk scores rise, validated tools such as the Revised Cardiac Risk Index help teams weigh the need for further imaging (Lee et al. 1999). Pulmonary risk follows the same logic. Researchers identified predictable factors for postoperative respiratory complications, which supports selective rather than universal testing (Gupta et al. 2012).
Assessment | What it shows | When it is typically ordered |
Electrocardiogram (ECG) | Heart rhythm and electrical conduction | Most candidates as a baseline |
Echocardiogram | Heart structure and pumping function | Known cardiac disease or murmur |
Cardiac stress testing | Blood flow under exertion | Symptoms or high risk scores |
Chest X-ray | Heart size, lungs, diaphragm | Specific clinical questions |
Pulmonary function tests | Breathing capacity | Existing lung disease such as COPD or asthma |
These evaluations matter most when they change management, such as adjusting fluid plans or planning intensive monitoring after surgery. One breathing-related condition deserves its own discussion, because obesity and sleep-disordered breathing overlap so strongly.
Is a Sleep Study Necessary Before Bariatric Surgery?

Not every patient needs polysomnography. Programs screen with questionnaires first, then order a sleep study for people with snoring, witnessed breathing pauses, daytime sleepiness, or high-risk features.
Obesity raises the prevalence of obstructive sleep apnea dramatically, and unrecognized apnea complicates airway management and pain control with opioids. In a large surgical cohort, investigators found unrecognized sleep apnea carried meaningful perioperative implications, which motivated routine screening strategies (Kaw et al. 2006). Polysomnography monitors breathing effort, oxygen saturation, and heart rate through the night. Portable polygraphy at home offers a less invasive alternative, and a direct comparison found both methods detect clinically relevant disease, although home testing can miss mild cases (van Veldhuisen et al. 2022).
Evidence also supports selectivity. A retrospective cohort of more than 500 bariatric patients found that universal polysomnography did not reduce cardiopulmonary complications, so the authors advised testing at the individual level (Blume et al. 2022). When apnea is confirmed, clinicians plan airway technique, postoperative observation, and CPAP therapy in advance. Once breathing risks are mapped, the team examines the digestive tract itself.
What Digestive System Tests Are Performed Before Bariatric Surgery?
Upper gastrointestinal endoscopy is the central investigation. Contrast studies, abdominal ultrasound, and Helicobacter pylori testing are added selectively based on symptoms and findings.
Endoscopy lets the surgeon inspect the esophagus, stomach, and duodenum before altering that anatomy. The examination can reveal inflammation, ulcers, polyps, or a hiatal hernia that changes the surgical plan. Research supports its value in bariatric candidates, since findings frequently modify management (Corcelles et al. 2014). An abdominal ultrasound evaluates the gallbladder, because obesity and rapid weight loss both promote gallstones. H. pylori testing and treatment may reduce ulcer risk afterward, depending on local practice.
Findings carry direct consequences for procedure selection. Significant gastroesophageal reflux or a sizable hiatal hernia often pushes the team toward gastric bypass rather than sleeve gastrectomy, because the bypass anatomy reduces acid exposure. These gastrointestinal results then join the laboratory data in the final clearance decision, which also depends on two non-laboratory evaluations.
Are Psychological and Nutritional Evaluations Required Before Surgery?
Yes. Accredited programs treat psychological assessment and dietitian consultation as mandatory components of bariatric surgery clearance, even though they involve no needles or scans.
These are structured clinical interviews, not pass-or-fail exams. The psychological evaluation explores emotional readiness, expectations, eating behaviors, and substance use history. The dietitian reviews dietary patterns, identifies deficiency risks from the food history, and builds the postoperative meal plan. Guidelines emphasize that psychosocial factors strongly influence long-term adherence, weight outcomes, and emotional adjustment (Mechanick et al. 2020).
The behavioral assessment also verifies practical readiness. Can the patient commit to vitamin supplementation, protein targets, physical activity, and lifelong follow-up appointments? When the team identifies concerns such as binge eating or untreated depression, it arranges treatment first. Surgery follows stabilization, not the other way around. Beyond these universal evaluations, some candidates need targeted investigations tied to their personal history.
Which Additional Tests Depend on Your Medical History?
Endocrine workups, cardiology or pulmonology consultations, and gastroenterology referrals are ordered selectively, driven by symptoms, previous diagnoses, or family history.
No program tests everything on everyone. A patient with irregular menstrual cycles and rapid weight gain may receive endocrine studies to rule out hormonal disorders. Someone with established heart failure sees a cardiologist before anesthesia clearance. Persistent reflux or abnormal digestive imaging triggers gastroenterology input. Age-appropriate cancer screening, such as colonoscopy, follows routine preventive guidelines rather than bariatric rules.
This selective approach protects you from unnecessary procedures and cost. It also explains why two candidates at the same clinic can face different workups. Your personal risk profile, not a fixed list, determines the final menu of tests, and the planned operation adds another layer of variation.
Do Gastric Sleeve and Gastric Bypass Require Different Preoperative Tests?
The core laboratory panel overlaps heavily between procedures. Malabsorptive operations such as gastric bypass demand broader micronutrient testing, while digestive findings like reflux or hiatal hernia can steer the choice of operation itself.
Restrictive procedures, mainly sleeve gastrectomy, reduce stomach size while preserving normal absorption routes. Malabsorptive procedures, principally Roux-en-Y gastric bypass, reroute digestion and raise deficiency risk for iron, calcium, and B12. Guidelines therefore recommend more extensive biochemical monitoring for bypass candidates (O'Kane et al. 2020). Endoscopy findings also influence selection, since pre-existing reflux favors bypass anatomy over a sleeve.
Factor | Gastric bypass | |
Core blood tests | Required | Required |
Extended micronutrient panel | Sometimes | Usually more comprehensive |
Endoscopy emphasis | Reflux and hernia assessment | Reflux, hernia, and ulcer risk assessment |
Typical nutritional risk profile | Moderate | Higher for iron, calcium, B12 |
Sleep and cardiac screening | Symptom-based | Symptom-based |
Because risk profiles differ, your team tailors testing to the procedure under discussion. Timing, however, follows a predictable pattern across programs.
How Long Before Bariatric Surgery Should You Complete the Tests?
Begin the evaluation four to eight weeks before your planned date, and confirm validity windows with your program, since many hospitals accept results only within a set number of days.
The workup takes time because abnormal findings create new tasks. A low ferritin level needs weeks of supplementation and a repeat draw. Suspected sleep apnea requires a study and CPAP titration. Blood pressure or glucose optimization may extend the timeline further. Starting early prevents scheduling delays, and it gives every specialist room to respond.
Ask your coordinator how long each result stays valid. A common window ranges from 30 to 90 days, but policies vary by institution. A smooth timeline also depends on how well you prepare for each appointment.
How Should You Prepare for Preoperative Bariatric Tests?
Gather your medical records, medication and supplement lists, and insurance information, then follow fasting instructions and disclose your full health history to every specialist.
Preparation is simple but consequential. Bring prior laboratory results, imaging reports, and operation notes, because old data can prevent duplicate testing. Ask whether you need to fast before blood draws or ultrasound appointments, since food affects glucose and lipid readings. Tell the team about allergies, previous anesthesia problems, smoking, and all medical conditions, including ones that seem unrelated to weight.
Never stop prescribed medication on your own. Some drugs, particularly blood thinners and certain diabetes medications, need timed adjustments, but only your prescribing clinician should direct those changes. Finally, attend every scheduled nutrition, psychological, and specialist visit, because each one contributes to the final clearance decision. Even careful preparation sometimes surfaces abnormal results, and that situation has a well-defined path.
What Happens If Your Preoperative Test Results Are Abnormal?
Most abnormal findings delay surgery temporarily while the team treats the underlying issue. Very few results disqualify a candidate permanently.
Each abnormality maps to a response. Anemia or low ferritin triggers iron therapy and repeat testing. Elevated glucose leads to medication changes and better control before clearance. Suspected sleep apnea prompts a study and CPAP planning. Heart rhythm concerns generate cardiology consultation. Surgery proceeds once the risk reaches an acceptable level, because the goal is optimization, not perfection.
An abnormal result can feel discouraging, but it usually protects you. Treating a deficiency before surgery costs weeks; treating it after surgery costs far more in recovery and complications. The same logic applies to the final checklist your team reviews before the operation date.
Frequently Asked Questions About Bariatric Surgery Testing
What Is the Most Important Test Before Bariatric Surgery?
No single test decides readiness. Your team reviews the combined picture from laboratory work, imaging, and specialist assessments before granting bariatric surgery clearance.
Are Blood Tests Mandatory Before Gastric Sleeve Surgery?
Yes. Blood work is a standard component of gastric sleeve pre-op tests everywhere, although the exact panel varies by patient and program.
Does Everyone Need an Endoscopy Before Gastric Bypass?
No. Endoscopy requirements vary by symptoms, clinical findings, surgical practice, and local guidelines, so confirm the policy at your center.
Can Bariatric Surgery Be Delayed Because of Abnormal Blood Results?
Yes, when a result needs treatment or investigation to protect your safety. Most delays are temporary, and the team reschedules once values improve.
How Many Medical Appointments Are Needed Before Weight Loss Surgery?
Expect at least five to eight visits, including laboratory draws, dietitian and psychological consultations, and specialist evaluations, though complex histories require more.
Are Preoperative Tests Covered by Insurance?
Coverage depends on your plan, local healthcare rules, and medical necessity. Ask your insurer and bariatric coordinator to verify benefits before testing begins.
Final Checklist for Bariatric Surgery Preoperative Testing
Complete all laboratory and nutritional testing, finish required specialist and behavioral evaluations, resolve abnormal findings, and obtain written clearance before your operation date.
Step | Status to confirm |
Blood panel and bariatric blood work | Complete and reviewed |
Vitamin and mineral screening | Complete, deficiencies treated |
Cardiac, respiratory, and sleep assessments | Done as indicated |
Endoscopy and digestive imaging | Done as indicated |
Psychological and dietitian evaluations | Complete |
Abnormal results addressed | Treatment plan followed |
Final preoperative medical clearance | Signed by your team |
Understanding what tests are needed before bariatric surgery removes uncertainty from the process. A structured preoperative evaluation measures your health today, protects you during surgery, and creates the benchmarks that guide your care for years afterward. Bring your questions to your bariatric team, complete each step in order, and treat the workup as the first investment in your long-term result.
References
Ben-Porat, T., et al. "Nutritional Deficiencies Four Years After Sleeve Gastrectomy." Obesity Surgery, vol. 25, no. 10, 2015, pp. 1899-1902.
Blume, Claudia A., et al. "Polysomnography in Pre-Operative Screening for Obstructive Sleep Apnea in Patients Undergoing Bariatric Surgery: A Retrospective Cohort Study." International Journal of Obesity, vol. 46, 2022.
Chang, Su-Hsin, et al. "Early Major Complications After Bariatric Surgery in the USA, 2003-2014: A Systematic Review and Meta-Analysis." Obesity Reviews, vol. 19, no. 4, 2018, pp. 529-537.
Corcelles, Ricard, et al. "The Value of Routine Preoperative Upper Endoscopy in Bariatric Surgery." Surgery for Obesity and Related Diseases, vol. 10, no. 2, 2014, pp. 222-225.
Flum, David R., et al. "Perioperative Safety in the Longitudinal Assessment of Bariatric Surgery." New England Journal of Medicine, vol. 361, no. 5, 2009, pp. 445-454.
Gupta, Prateek K., et al. "Predictors of Pulmonary Complications After Bariatric Surgery." Surgery for Obesity and Related Diseases, vol. 8, no. 5, 2012, pp. 574-581.
Kaw, Roop, et al. "Unrecognized Sleep Apnea in the Surgical Patient: Implications for the Perioperative Setting." Chest, vol. 129, no. 1, 2006, pp. 198-205.
Lee, Thomas H., et al. "Derivation and Prospective Validation of a Simple Index for Prediction of Cardiac Risk of Major Noncardiac Surgery." Circulation, vol. 100, no. 10, 1999, pp. 1043-1049.
Mechanick, Jeffrey I., et al. "Clinical Practice Guidelines for the Perioperative Nutrition, Metabolic, and Nonsurgical Support of Patients Undergoing Bariatric Procedures: 2019 Update." Surgery for Obesity and Related Diseases, vol. 16, no. 2, 2020, pp. 175-247.
O'Kane, Mary, et al. "British Obesity and Metabolic Surgery Society Guidelines on Perioperative and Postoperative Biochemical Monitoring and Micronutrient Replacement for Patients Undergoing Bariatric Surgery: 2020 Update." Obesity Reviews, vol. 21, no. 11, 2020, e13087.
van Veldhuisen, Sophie L., et al. "Preoperative Assessment of Obstructive Sleep Apnea in Bariatric Patients Using Polysomnography or Polygraphy." Obesity Surgery, vol. 32, no. 6, 2022, pp. 1814-1821.